

Knee pain that once appeared only after long walks or physical effort can gradually become a constant companion — even at rest, even at night. If you’ve already tried medication, physical therapy, and injections without lasting relief, you may be wondering whether knee replacement surgery is the next step. The answer depends not on a single symptom, but on a combination of objective signs that reflect how severely osteoarthritis is affecting your daily life and whether conservative treatments have truly been exhausted.
This article explains the concrete, observable signs that suggest it may be time to discuss knee replacement with a specialist, the diagnostic process that confirms the need, and the treatment options available at each stage. The goal is to help you prepare an informed conversation with your doctor — not to replace that conversation.
What Is Knee Replacement Surgery and When Is It Considered?
Knee replacement surgery, medically known as knee arthroplasty, is a procedure in which a surgeon removes damaged portions of the knee joint and replaces them with artificial components made of metal and plastic. The goal is to restore pain-free movement when the natural joint has deteriorated beyond what nonsurgical treatments can manage.
This deterioration is most commonly caused by knee osteoarthritis, a progressive condition in which the protective cartilage cushioning the ends of the bones gradually wears away. As cartilage breaks down, bones begin to rub against each other, causing pain, stiffness, swelling, and eventually significant loss of mobility. According to the Osteoarthritis Action Alliance, osteoarthritis affects approximately 32.5 million American adults, and more than half of people with knee osteoarthritis will undergo total knee replacement at some point in their lives.
Knee replacement is not a first-line treatment. Before surgery is even discussed, doctors typically recommend a progression of conservative therapies: nonsteroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen or naproxen, corticosteroid or hyaluronic acid injections, weight management, assistive devices like canes or walkers, and physical therapy to strengthen the muscles around the knee and improve range of motion. Surgery becomes a conversation worth having when these approaches, applied consistently and correctly, no longer provide meaningful relief.
As Prof. Etienne Cavaignac emphasizes in his clinical practice, the decision to proceed with knee replacement surgery is always individual and must be based on a combination of clinical evaluation, imaging results, and the patient’s own functional goals and quality of life. There is no arbitrary age cutoff or single threshold that automatically triggers surgery; rather, it is a shared decision between patient and surgeon, informed by objective medical criteria.
Signs That Non-Surgical Treatments Are No Longer Enough
Direct answer: The clearest signs that conservative treatments may no longer be sufficient include persistent knee pain that does not improve with medication and physical therapy, pain that disrupts sleep, difficulty walking more than a few blocks or climbing stairs without significant discomfort, and radiographic evidence of advanced joint damage. These signs, taken together, suggest it may be time to consult an orthopedic specialist about your treatment options.
Knowing when to move from conservative management to a surgical discussion requires you to observe not just whether you have pain, but how that pain affects your daily activities and whether it responds to the treatments you’ve tried. The following are concrete, measurable signs that conservative treatments may be reaching their limits.
First, pain that persists despite appropriate use of NSAIDs and completion of a structured physical therapy program is a key indicator. This does not mean occasional discomfort after unusually strenuous activity; it means pain that is present most days, limits your ability to do routine tasks, and does not improve with rest, medication, or therapeutic exercise. If you have been diligent with physical therapy for several months and find that your pain remains constant or worsens, that is a signal worth discussing with a specialist.
Second, pain that wakes you up at night or prevents you from finding a comfortable sleeping position is a red flag. In the early stages of knee osteoarthritis, pain typically occurs with activity and subsides with rest. When pain becomes severe enough to disturb sleep, it often indicates advanced cartilage loss and inflammatory changes in the joint. The American Academy of Orthopaedic Surgeons notes that pain appearing even in sitting or lying positions is a hallmark of later-stage osteoarthritis and a common reason patients and doctors begin discussing surgical options.

Third, specific limitations in mobility serve as practical benchmarks. If you find yourself unable to walk more than a block or two without needing to stop and rest because of knee pain, if you avoid stairs whenever possible because descending causes sharp pain, or if you have stopped activities you previously enjoyed — gardening, shopping, playing with grandchildren — because your knee cannot tolerate them, these are functional losses that matter. They reflect not just discomfort, but a measurable decline in independence and quality of life.
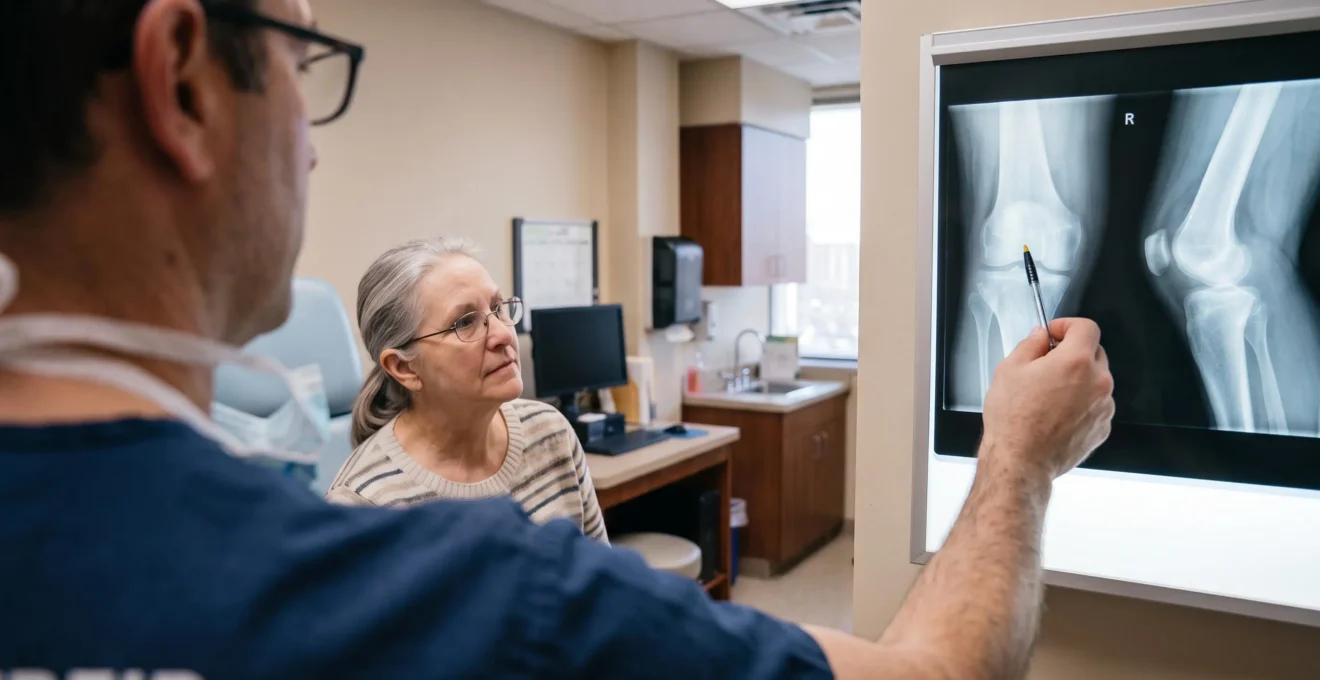
Fourth, X-rays and other imaging studies provide objective evidence of joint damage. While pain is subjective, radiographs can show the extent of cartilage loss, narrowing of the joint space, bone spurs, and bone-on-bone contact. Your doctor will review these images with you and explain what they reveal about the severity of your osteoarthritis. However, it is important to understand that imaging alone does not determine whether you need surgery; a person can have severe X-ray findings but still function well enough that surgery is not yet warranted, while another person with moderate imaging findings may have debilitating pain that justifies surgical intervention. The combination of symptoms, functional limitations, and radiographic findings guides the decision.
When to seek urgent evaluation: If you experience sudden onset of severe knee pain, significant swelling, fever, inability to bear weight, or a knee that gives way or locks in place, contact a healthcare provider promptly. These may indicate complications or conditions requiring immediate attention.
When Is It Time to Talk to a Specialist About Surgery?
Deciding when to consult an orthopedic surgeon involves recognizing that your current treatment plan is no longer meeting your needs. Typically, this conversation is appropriate when you have completed at least several months of conservative therapy — including medication, physical therapy, weight management if applicable, and possibly injections — and your pain and functional limitations remain significant.
During a specialist evaluation, the surgeon will perform a detailed clinical examination of your knee, assessing range of motion, stability, alignment, and areas of tenderness. The surgeon will review your imaging studies, including X-rays and possibly MRI if additional detail is needed. Importantly, the surgeon will ask about your daily activities, your goals, and how knee pain is affecting your life. This is not a one-sided assessment; you are an active participant in the decision-making process.
Research on the appropriateness of knee replacement, including a study published in Osteoarthritis and Cartilage, has shown that surgical decision-making relies on a combination of traditional clinical variables: patient age, severity of knee osteoarthritis, radiographic pattern, and knee range of motion. Notably, pain reported by the patient alone does not solely drive the appropriateness rating for surgery; rather, the decision rests on integrating multiple objective and subjective factors.
Timing matters. Operating too early — before conservative treatments have been adequately tried — means undergoing major surgery that might have been avoided or delayed. Operating too late — after years of compensatory movement patterns, muscle atrophy, and worsening bone alignment — can complicate recovery and limit the ultimate functional outcome. The goal is to find the window in which surgery offers the best balance of risk and benefit, preserving bone quality and muscle strength while relieving pain that genuinely interferes with daily life.
- If pain persists after 3–6 months of appropriate conservative treatment:
Schedule an evaluation to discuss whether your current treatment plan should be adjusted or whether surgical options are worth exploring.
- If you experience night pain or pain at rest despite medication:
This often signals advanced joint damage and warrants a specialist review of your imaging and symptoms.
- If daily activities are significantly restricted:
Difficulty walking short distances, climbing stairs, or performing routine tasks suggests your knee function is declining enough to justify a surgical discussion.
- If you have questions about your X-ray or MRI findings:
A specialist can explain what the images mean, how they relate to your symptoms, and what treatment options are available at your stage of osteoarthritis.
What to Expect: Treatment Options and Personalized Care
Not everyone with advanced knee osteoarthritis proceeds directly to total knee replacement. Depending on your age, activity level, the pattern of cartilage damage, and your overall health, several treatment pathways may still be available.
If your arthritis is localized to one compartment of the knee — for example, only the inner (medial) side is severely damaged — you may be a candidate for a partial knee replacement, also called unicompartmental arthroplasty, which replaces only the affected portion and preserves healthy tissue. Younger, active patients with isolated arthritis and good bone alignment may also be candidates for an osteotomy, a procedure that reshapes the bone to shift weight away from the damaged area, potentially delaying the need for joint replacement by several years.
If arthritis affects multiple compartments of the knee or if conservative measures and limited surgical options have been exhausted, total knee replacement — in which the entire joint surface is resurfaced with prosthetic components — becomes the most reliable option for long-term pain relief and restored function. The choice among these options is highly individual and depends on a thorough evaluation by your surgeon.
Once a treatment plan is agreed upon, many orthopedic practices now offer personalized follow-up and support to help patients navigate the preoperative and postoperative periods. Some surgeons provide access to digital patient follow-up platforms, such as Orthense, which allow for structured communication, guided recovery exercises, symptom tracking, and timely responses to questions. These tools are offered as part of the surgeon’s care pathway and are designed to improve adherence to rehabilitation protocols and reduce anxiety during recovery.
Before making any decision, prepare a list of questions for your consultation. Consider asking your surgeon: How severe is my osteoarthritis based on the imaging? What are the realistic benefits and risks of surgery in my specific case? How long is the typical recovery, and what does rehabilitation involve? What happens if I choose to wait — will my condition worsen, and if so, how quickly? Are there alternative procedures I should consider? What are the expected outcomes in terms of pain relief, mobility, and return to activities? Having these answers will help you weigh your options with confidence.
FAQ: Common Questions About Knee Replacement Timing
How do I know if my knee osteoarthritis is bad enough for surgery?
Severity is assessed by combining your symptoms, functional limitations, and imaging findings. If you have persistent pain despite appropriate conservative treatment, difficulty performing daily activities like walking or climbing stairs, and X-rays showing significant joint damage, these together suggest your osteoarthritis may be advanced enough to discuss surgery. Only a specialist evaluation can confirm whether you are a candidate.
Is it normal for knee arthritis pain to wake me up at night, and what does it mean?
Night pain or pain at rest is not typical of early osteoarthritis and usually indicates more advanced joint deterioration. It is a red flag that warrants evaluation by an orthopedic specialist, as it often signals that conservative treatments are no longer controlling inflammation and that surgical options may need to be considered.
What happens if I wait too long to have knee replacement surgery?
Delaying surgery for many years can lead to muscle weakness, poor movement patterns, worsening bone alignment, and greater overall deconditioning, all of which can make recovery more challenging. Additionally, prolonged immobility and pain can reduce quality of life and independence. However, every case is different, and the decision about timing should be made with your surgeon based on your specific circumstances.
Can knee replacement be avoided with physical therapy and injections?
For some people, physical therapy, weight management, medications, and injections can effectively manage symptoms for many years, delaying or even avoiding the need for surgery. For others, especially those with advanced cartilage loss and bone-on-bone contact, these measures provide only temporary or partial relief. The goal of conservative treatment is to maximize function and comfort as long as possible; if it stops working, surgery becomes a reasonable next step.
What questions should I ask my doctor before deciding on knee replacement?
Ask about the severity of your arthritis based on imaging, the expected benefits and risks of surgery in your case, the recovery timeline, what rehabilitation will involve, what happens if you delay, whether there are alternative surgical options like partial replacement or osteotomy, and what realistic outcomes you can expect in terms of pain relief and return to activities.
Do X-rays alone determine if I need knee replacement surgery?
No. X-rays provide important information about the structural condition of your knee, but they are only one part of the decision. Your symptoms, functional limitations, response to conservative treatments, overall health, and personal goals all play a role. Some people with severe X-ray findings manage well without surgery, while others with moderate findings may be significantly disabled by pain and dysfunction.
Am I too young or too old for knee replacement surgery?
There is no absolute age cutoff. Younger patients may be encouraged to try all conservative options first and consider alternative procedures like osteotomy because knee implants have a finite lifespan and younger patients are more likely to need revision surgery eventually. Older patients are evaluated based on overall health, life expectancy, and ability to tolerate surgery and rehabilitation. Age is one factor among many; functional status and medical fitness matter more.
Key points to remember
- Knee replacement surgery is considered when conservative treatments — medication, physical therapy, injections — no longer provide meaningful relief and daily activities are significantly limited.
- Observable signs include persistent pain despite treatment, night pain, difficulty walking or climbing stairs, and radiographic evidence of advanced joint damage.
- The decision to proceed with surgery is individual and based on a combination of clinical examination, imaging, functional limitations, and patient goals — not pain alone.
- Alternatives such as partial knee replacement or osteotomy may be appropriate depending on age, activity level, and the pattern of arthritis.
- Consulting a specialist when symptoms worsen allows for a timely, informed discussion about the full range of treatment options and the best timing for intervention.
Understanding your body’s signals and knowing when conservative measures are no longer enough is an essential skill in managing chronic knee osteoarthritis. Paying attention to how pain affects your sleep, your mobility, and your independence — and tracking whether treatments that once helped are now falling short — gives you the objective evidence you need to have a meaningful conversation with a specialist. Learning to recognize early warning signs of your body can empower you to seek help at the right time, neither too early nor too late, so that any decision about surgery is made with clarity and confidence.
Medical Disclaimer: This article is provided for informational and educational purposes only and does not constitute medical advice. Knee replacement surgery is a major medical decision that must be made in consultation with a qualified orthopedic surgeon after a thorough individual evaluation. Do not use this information to self-diagnose or to delay seeking professional medical care. Always consult your healthcare provider with questions about your specific condition and treatment options.